OBJECTIVE:
To compare the rate of tolerance acquisition in Mexican infants with IgE-mediated cow's milk protein allergy, fed according to three dietary regimens.
METHODS:
A retrospective, observational cohort study was conducted on infants diagnosed with cow's milk protein allergy between 1 and 3 months of age, divided into three groups according to their feeding regimen: 1) exclusive breastfeeding with an elimination diet, 2) amino acid-based formula, and 3) hydrolyzed rice formula. Clinical characteristics, wheal size in skin prick tests against casein, alpha-lactalbumin, and beta-lactoglobulin, adherence to treatment, and coexisting allergic comorbidities were evaluated. Tolerance acquisition was determined by an open oral challenge test with whole milk after 12 months on an elimination diet. Comparative analyses and multivariate logistic regression were performed to identify associated factors.
RESULTS:
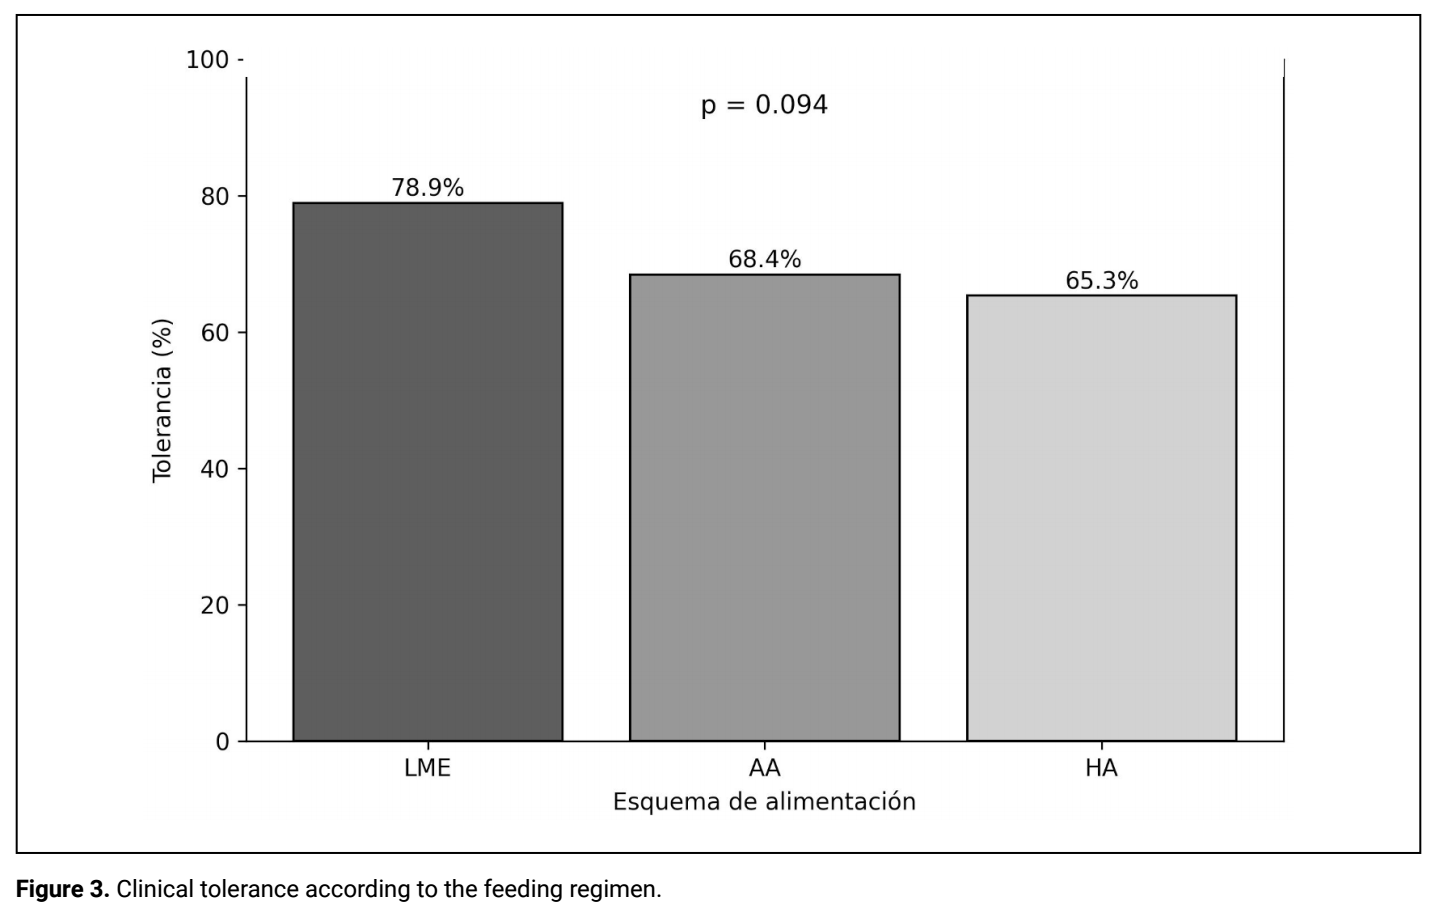
285 infants were selected and assigned to one of three study groups (n = 95 per group). 62.1% achieved clinical tolerance at the end of the follow-up period. The highest proportion was observed in the exclusive breastfeeding group (78.9%), followed by the amino acid-based formula group (68.4%) and the hydrolyzed rice formula group (65.3%), with no statistically significant differences between the regimens (p = 0.094). Adherence to the dietary treatment was significantly associated with the acquisition of tolerance in the multivariate model, while allergic comorbidities were associated with a lower probability of clinical cure.
CONCLUSIONS:
The elimination diet is associated with the acquisition of tolerance in a considerable proportion of infants with IgE-mediated cow's milk protein allergy. Although no superiority was identified among the dietary regimens, the findings suggest that adherence to treatment plays a determining role in clinical outcomes and should be considered a central component in the management of the disease.
OBJETIVO:
Comparar la tasa de adquisición de tolerancia en lactantes mexicanos con alergia a la proteína de leche de vaca mediada por IgE, alimentados con tres esquemas dietéticos.
MÉTODOS:
Estudio observacional, retrospectivo, de tipo cohorte, efectuado en lactantes diagnosticados con alergia a la proteína de leche de vaca entre 1 y 3 meses de edad, distribuidos en tres grupos según el esquema de alimentación: 1) lactancia materna exclusiva con dieta materna de eliminación, 2) fórmula con aminoácidos y 3) fórmula hidrolizada de arroz. Se evaluaron las características clínicas, tamaño del habón en las pruebas cutáneas frente a caseína, alfa-lactoalbúmina y beta-lactoglobulina, apego al tratamiento y coexistencia de comorbilidades alérgicas. La adquisición de tolerancia se determinó mediante la prueba de provocación oral abierta con leche entera después de 12 meses de dieta de eliminación. Se realizaron análisis comparativos y regresión logística multivariada para identificar los factores asociados.
RESULTADOS:
Se seleccionaron 285, asignados a uno de los tres grupos de estudio (n = 95 por grupo). El 62.1% tuvo tolerancia clínica al final del seguimiento. La mayor proporción se observó en el grupo de lactancia materna exclusiva (78.9%), seguido de fórmula con aminoácidos (68.4%) y fórmula hidrolizada de arroz (65.3 %), sin diferencias estadísticamente significativas entre los esquemas (p = 0.094). El apego al tratamiento dietético se asoció significativamente con la adquisición de tolerancia en el modelo multivariado, mientras que las comorbilidades alérgicas se relacionaron con menor probabilidad de curación clínica.
CONCLUSIONES:
La dieta de eliminación se asocia con adquisición de tolerancia en una proporción considerable de lactantes con alergia a la proteína de leche de vaca mediada por IgE. Aunque no se identificó superioridad entre los esquemas dietéticos, los hallazgos sugieren que el apego al tratamiento desempeña un papel determinante en la evolución clínica y debe considerarse un componente central en el tratamiento de la enfermedad.
BACKGROUND
Cow's milk protein allergy (CMPA) is one of the most frequent allergic diseases in childhood. Its global prevalence is estimated to range between 2% and 7.5% in infants under one year of age, although these figures depend on the type of population, diagnostic method, and criteria used.1,2,3,4 Of these cases, between 40% and 60% correspond to immunoglobulin E (IgE)-mediated forms, characterized by the rapid manifestation of symptoms after the consumption of milk proteins and a positive prick test.5,6
In Latin America, the prevalence of CMPA has been less documented, although various studies agree that it is within the same range as that reported globally. In countries such as Argentina, Brazil, and Chile, local research estimates an incidence between 2% and 5% in children under 1 year of age.7 In Mexico, epidemiological evidence has increased in recent decades. A cross-sectional study in university students in Guadalajara found a prevalence of 1.4%, while in the María Inmaculada Clinic in Mexico City, 650 cases were documented between 2010 and 2015 in children under 9 years of age.8 A recent analysis, published in Acta Pediátrica Mexicana, indicates that, despite greater diagnostic awareness, cases remain underestimated due to a lack of unified criteria and insufficient application of confirmatory tests such as the double-blind, placebo-controlled oral challenge.9
Although Mexico has national clinical guidelines and adheres to Latin American consensuses for CMPA treatment,10 there is still little local evidence with robust comparative designs evaluating the immunological effect of different feeding regimens and standardized follow-up.11,12,13 Most Mexican studies are simple observational studies or case reports that do not evaluate the evolution of sensitization or long-term tolerance rates.
The treatment of patients with CMPA, in both its IgE-mediated and non-IgE-mediated forms, is based on the total elimination of cow's milk proteins from the infant's diet.14,15 The most common dietary strategies include breastfeeding with an elimination diet, amino acid-based formulas, and hydrolyzed rice formulas. Recent studies have shown that amino acid formulas enriched with synbiotics can accelerate immunological tolerance. Likewise, it has been found that breastfeeding with strict exclusion of dairy can be effective in symptom control.16-19 In Mexico, rice formulas have been offered as a culturally accepted and clinically safe alternative.
Despite the recognition of these dietary strategies, there is little direct comparative evidence between them regarding the development of tolerance at 12 months of consumption. Factors such as adherence to the diet, cultural context, and clinical follow-up influence immunological evolution.
Cow's milk protein allergy usually appears during the first 12 months of life, coinciding with the introduction of infant formulas or complementary feeding. Symptoms of IgE-mediated CMPA include: urticaria, angioedema, vomiting, diarrhea, persistent crying, wheezing, or anaphylaxis.20 The main proteins involved are caseins and those from the whey (beta-lactoglobulin and alpha-lactalbumin). Casein is considered the most allergenic and thermostable, persisting even after pasteurization.21
Several studies have shown that CMPA, especially in its IgE-mediated form, can precede the development of other allergic diseases: atopic dermatitis, asthma, rhinitis, or food allergies, a phenomenon known as the "atopic march." Clinical follow-up of patients must consider this type of complex immunological evolution.22
This study aims to compare the tolerance rate in Mexican infants diagnosed with IgE-mediated cow's milk protein allergy, fed according to different regimens. This seeks to provide useful local evidence to guide clinical decision-making in the treatment of this disease and optimize available therapeutic resources.
METHODS
Retrospective, observational, analytical, and comparative cohort study, conducted in infants seen at a private pediatric allergy practice between January 2017 and December 2024. Patients aged 1 to 3 months with clinical suspicion of IgE-mediated cow's milk protein allergy and diagnostic confirmation with a positive skin prick test to one or more milk allergens (casein, alpha-lactalbumin, and beta-lactoglobulin) were selected, using standardized extracts with a current sanitary registration in Mexico (IPI ASAC®). All patients had a minimum clinical follow-up of 12 months. Patients with primary or secondary immunodeficiencies, metabolic disorders, chronic gastrointestinal diseases, loss to follow-up before 12 months, or combined use of more than one feeding regimen during the observation period were excluded.
Patients were grouped according to the dietary treatment prescribed into three cohorts: 1) exclusive breastfeeding (EBF; maternal diet free of dairy and traces), 2) amino acid-based formula (AA), and 3) hydrolyzed rice formula (HR). Assignment to the feeding regimen was based on clinical indication and family possibilities, so it was not randomized.
During the monthly follow-up, the following were recorded: wheal size in the baseline prick test at 12 months, adherence to dietary treatment, coexistence of allergic comorbidities (atopic dermatitis, rhinitis, infant wheezing, and conjunctivitis), and a family history of atopy in the first degree.
Adherence to treatment was classified as: good, fair, or poor through a retrospective review of clinical records, considering the dietary compliance reported by caregivers during follow-up consultations and the documentation of accidental exposures. This classification was performed independently of the oral challenge test result. No formal validated instrument was implemented for its measurement.
At the 12-month follow-up, an open oral food challenge test with whole milk was performed under the supervision of the pediatric allergist. The test was considered positive upon the appearance of clinical signs compatible with an immediate allergic reaction and negative in the absence of symptoms, interpreted as the acquisition of clinical tolerance.
A descriptive analysis was performed using frequencies, means, and standard deviations. Comparisons between groups were made using the χ² test for categorical variables and analysis of variance (ANOVA) for comparison of means. Comparisons between specific proteins using ANOVA were interpreted in an exploratory context, without formal correction for multiple comparisons. To identify factors associated with the acquisition of tolerance, a multivariate logistic regression model was constructed, expressing the results in odds ratios (OR) with 95% confidence intervals. The stability of the model was evaluated using the number of events per variable (>10), the Hosmer–Lemeshow test, and collinearity analysis. A p-value < 0.05 was considered statistically significant. IBM SPSS version 28 software and Python were used for statistical analysis.
RESULTS
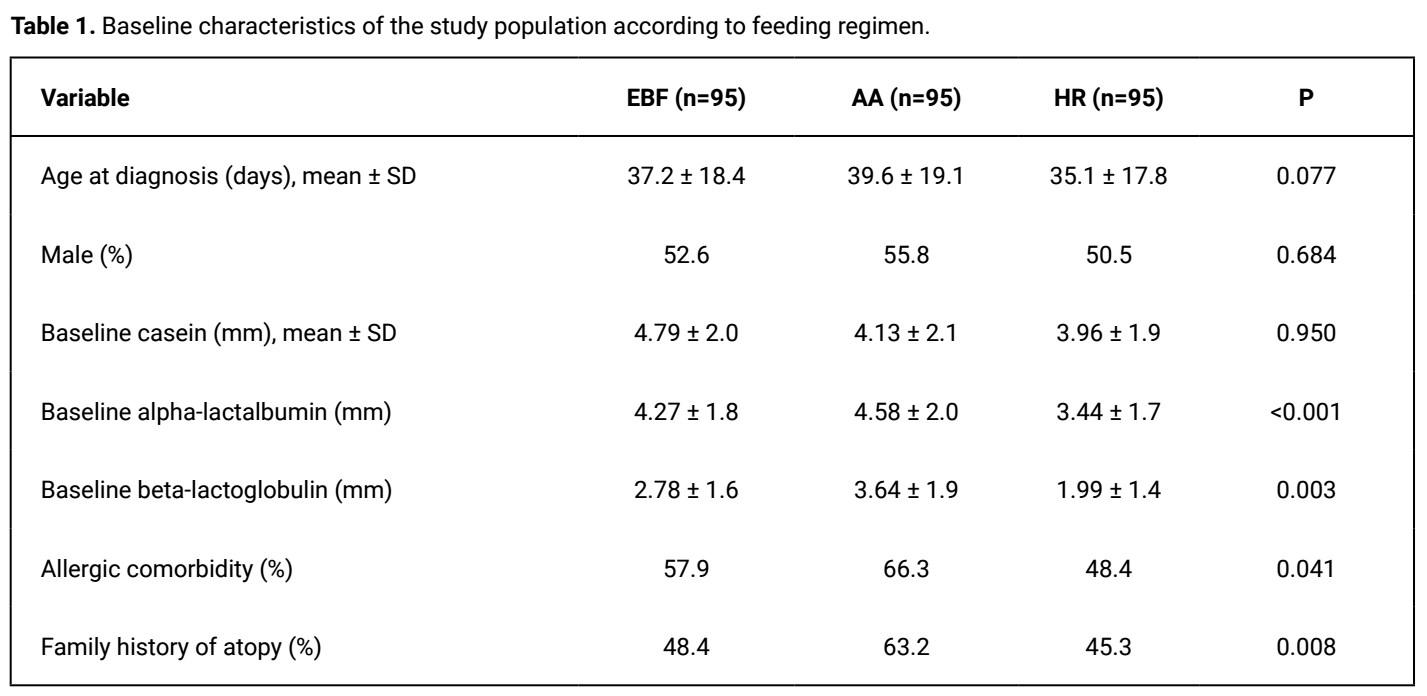
We analyzed 285 records of Mexican infants diagnosed with IgE-mediated cow's milk protein allergy, distributed equally into three feeding regimens (n = 95 per group). Baseline characteristics are shown in Table 1. No significant differences were observed between the groups regarding age at diagnosis (p = 0.077), gender distribution (p = 0.684), or baseline wheal size for casein (p = 0.950). In contrast, significant differences were identified in baseline values for alpha-lactalbumin (p < 0.001) and beta-lactoglobulin (p = 0.003), as well as in allergic comorbidities (p = 0.041) and family history of atopy (p = 0.008).
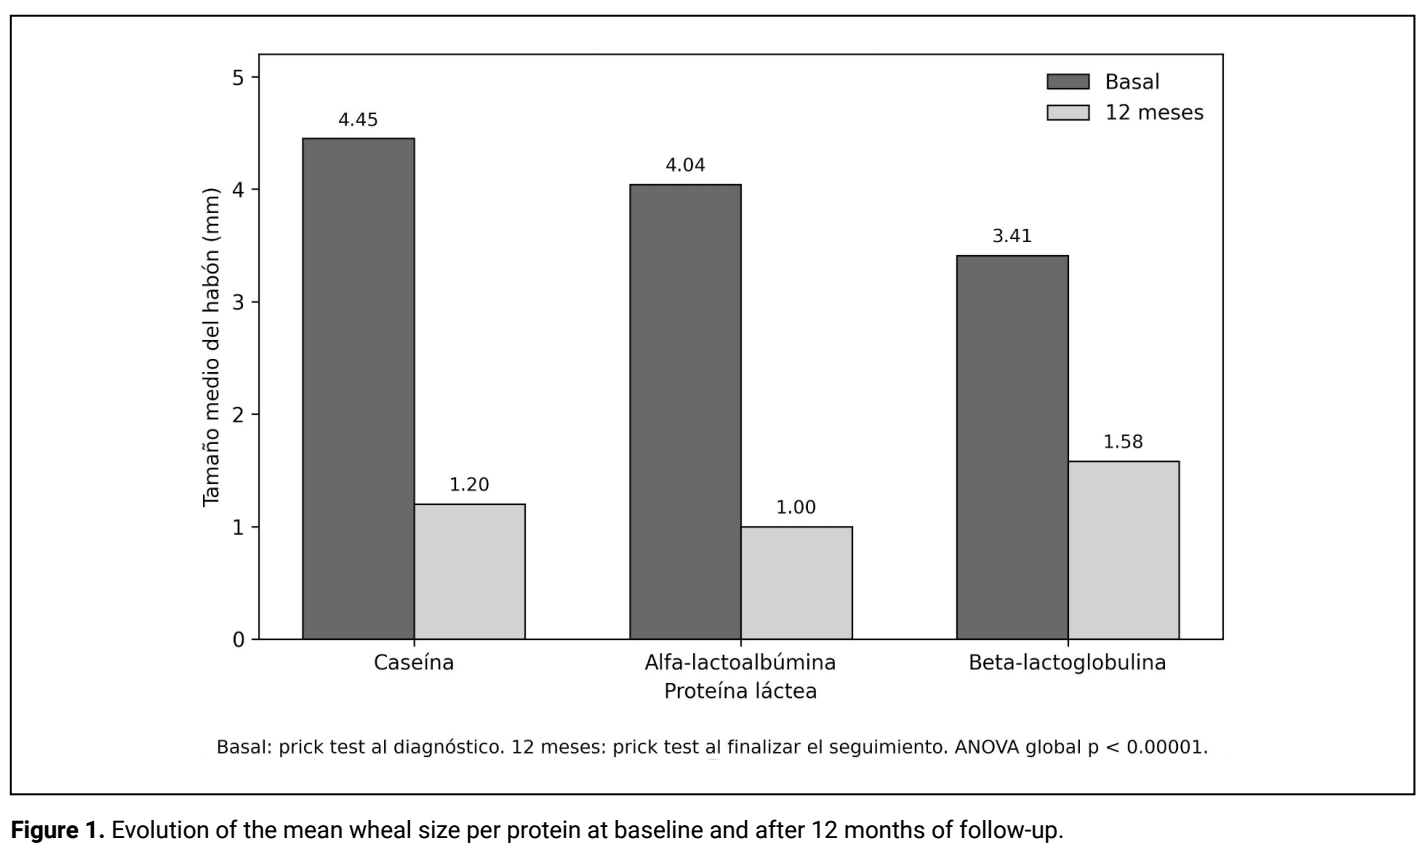
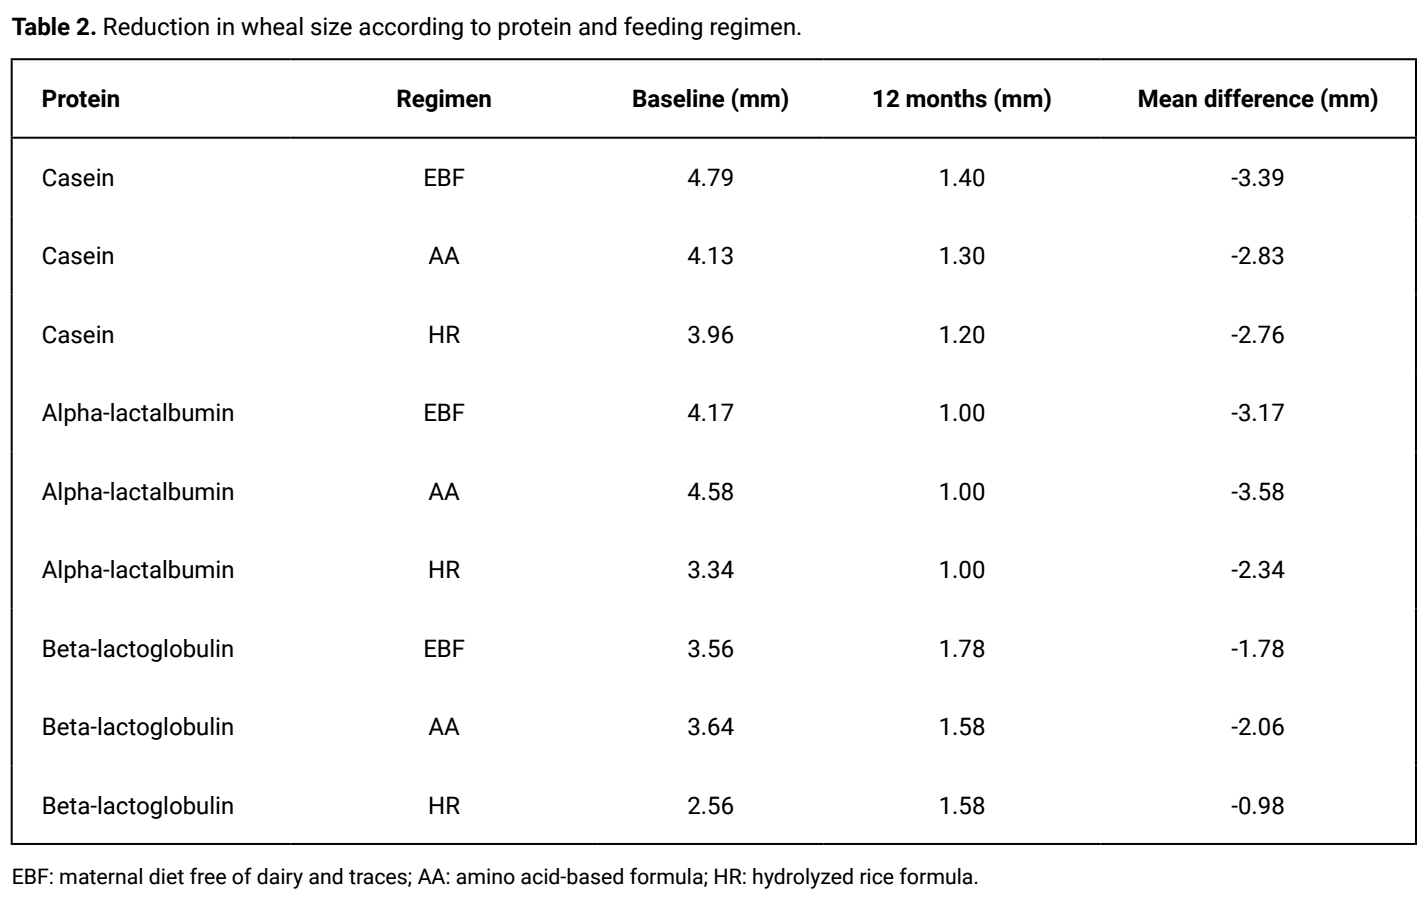
Casein was the protein with the highest initial skin reactivity, with an average wheal size of 4.45 mm, higher than that observed for alpha-lactalbumin (4.04 mm) and beta-lactoglobulin (3.41 mm); ANOVA, p < 0.00001. By feeding regimen, the highest baseline reactivity for casein was observed in the exclusive breastfeeding group (4.79 mm), followed by the group that received amino acid-based formula (4.13 mm) and hydrolyzed rice formula (3.96 mm). After 12 months of dietary intervention, the wheal size for this protein decreased to approximately 1.1–1.4 mm in all groups, with the largest absolute reduction in group 1 (−3.39 mm; Figure 1). For alpha-lactalbumin, the amino acid formula group showed the highest baseline reactivity (4.58 mm) and also the largest reduction (−3.58 mm), reaching an average value of 1.00 mm at 12 months. In the exclusive breastfeeding group, the reduction was −3.17 mm, while in the hydrolyzed rice formula group, it was −2.34 mm. Regarding beta-lactoglobulin, the group that received amino acid formula showed the largest decrease, going from 3.64 mm to 1.58 mm (−2.06 mm), compared to −1.78 mm in group 1 and −0.98 mm in group 3 (detailed values for wheal size reduction by protein and feeding regimen are shown in Table 2).
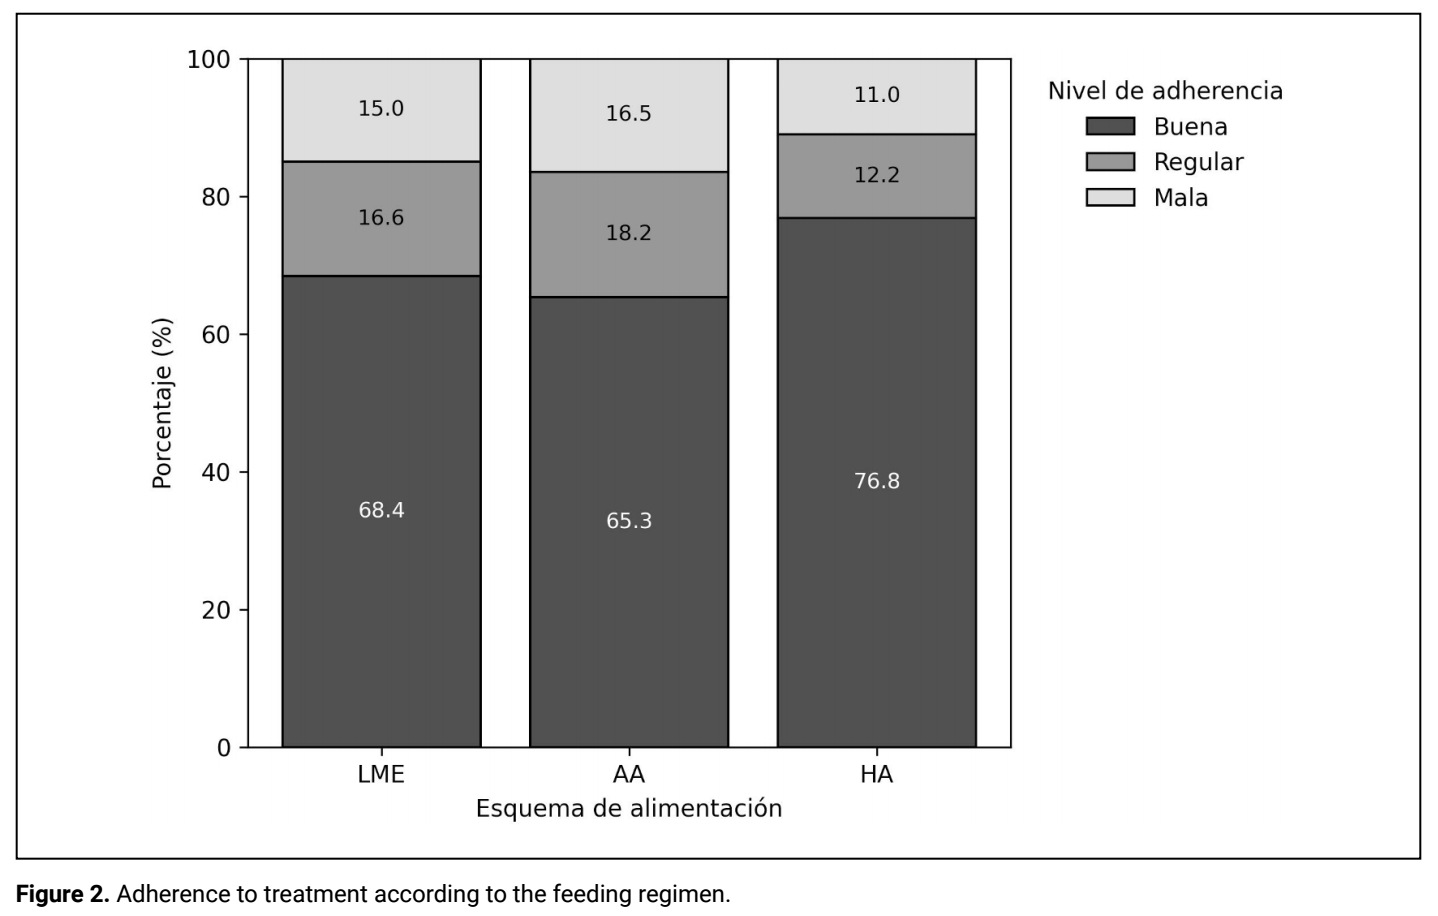
Adherence to dietary treatment was classified as good in 57.9% of cases, fair in 22.1%, and poor in 20%. The group that received hydrolyzed rice formula reported the highest proportion of good adherence (76.8%), compared to 68.4% in the breastfeeding group and 65.3% in the amino acid formula group (Figure 2).
At the 12-month follow-up, 62.1% of infants developed clinical tolerance, defined by a negative oral food challenge. The proportion of tolerance was 78.9% in the exclusive breastfeeding group, 68.4% in the amino acid formula group, and 65.3% in the hydrolyzed rice formula group; however, these differences did not reach statistical significance (χ² = 4.8; p = 0.094). Figure 3
The acquisition of tolerance showed a clear association with adherence to treatment. Tolerance rates were higher than 75% in patients with good adherence and lower than 25% in those who reported poor adherence, with statistical significance in all groups (p < 0.001 in groups 1 and 2; p = 0.019 in group 3).
Regarding allergic comorbidities, the most frequent were: atopic dermatitis (33.7%), wheezing (28.8%), allergic rhinitis (22.8%), and allergic conjunctivitis (11.9%), while 52.3% of patients had a family history of atopy. Allergic comorbidities were significantly associated with a lower probability of acquiring tolerance (p < 0.001), while family history of atopy showed no significant association with this outcome (p = 0.617).
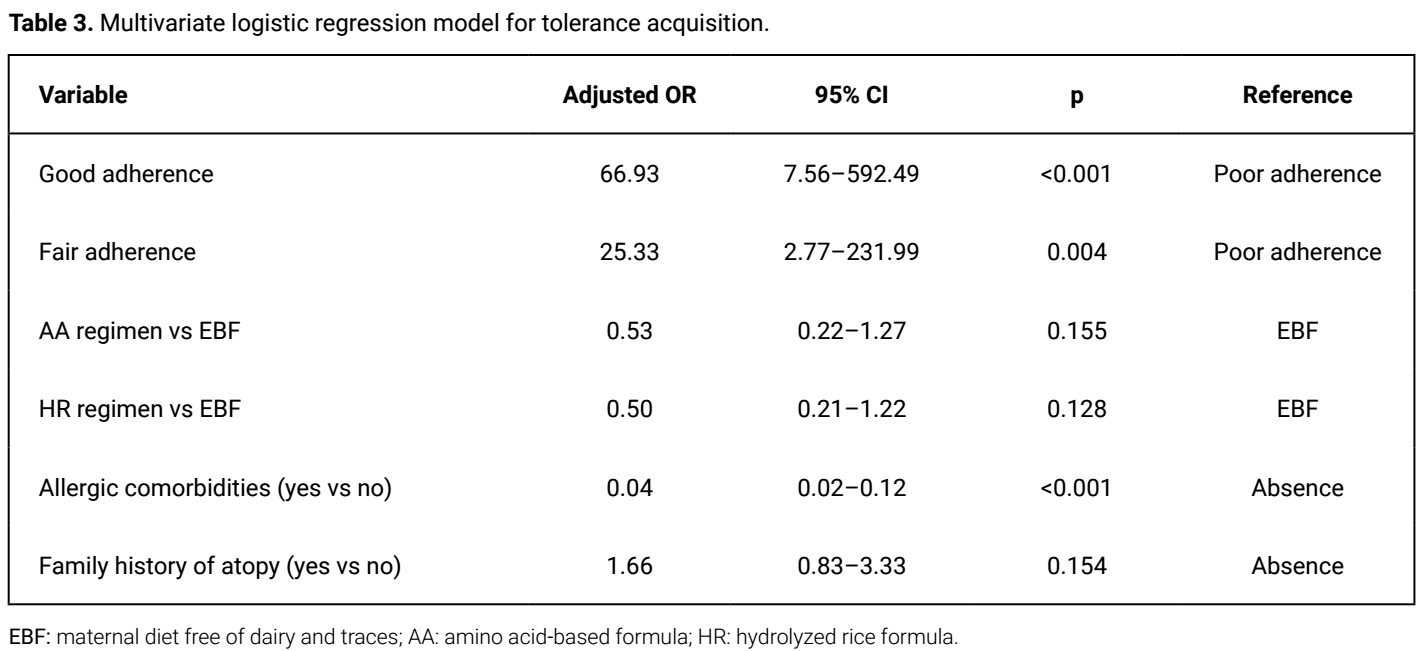
In the multivariate logistic regression model adjusted for age, gender, allergic comorbidities, and family history of atopy, adherence to treatment remained the main factor associated with the acquisition of tolerance. Compared with poor adherence, good adherence showed an adjusted OR of 66.93 (95% CI 7.56–592.49; p < 0.001), while fair adherence reported an OR of 25.33 (95% CI 2.77–231.99; p = 0.004). No statistically significant differences were observed between feeding regimens after multivariate adjustment (amino acid formula vs. exclusive breastfeeding: OR 0.53, 95% CI 0.22–1.27; p = 0.155; hydrolyzed rice formula vs. exclusive breastfeeding: OR: 0.50, 95% CI 0.21–1.22; p = 0.128).
Allergic comorbidities were associated with a lower probability of acquiring tolerance (OR: 0.04, 95% CI 0.02–0.12; p < 0.001), while family history of atopy showed no significant association (OR: 1.66, 95% CI 0.83–3.33; p = 0.154). The model showed adequate fit (Hosmer–Lemeshow test p = 0.83) and statistical stability, without evidence of relevant collinearity. Table 3
DISCUSSION
This study analyzed the clinical evolution of Mexican infants with IgE-mediated cow's milk protein allergy (CMPA) undergoing an elimination diet for 12 months. The proportion of tolerance acquisition observed is within the range reported in the international literature for early cure of the disease during the first years of life.23,24 However, since IgE-mediated CMPA shows a known rate of spontaneous recovery and the present study did not include a control group without dietary differentiation, it is not possible to determine precisely what proportion of the observed tolerance corresponds to the natural evolution of the disease.25 Consequently, the findings should be interpreted as observational associations and not as evidence of a direct causal effect of the feeding regimen.
In the descriptive analysis, a higher proportion of tolerance was observed in the group receiving exclusive breastfeeding, followed by amino acid-based formula and hydrolyzed rice formula. However, these differences did not reach statistical significance. Although this result prevents establishing superiority among the evaluated feeding regimens, the consistency of the observed pattern suggests a possible clinical trend that can be explored in prospective studies with controlled designs.
The reduction in the size of the skin wheal for the dairy proteins evaluated after 12 months of an elimination diet suggests a decrease in immediate IgE-mediated reactivity during clinical follow-up. Nevertheless, the prick test exclusively evaluates the immediate skin response and does not allow for inferring more complex changes in immunological memory. Therefore, these findings should be interpreted primarily as evidence of a decrease in immediate clinical reactivity and not as a direct demonstration of systemic immunological modification.
The multivariate analysis identified adherence to dietary treatment as the factor most strongly associated with tolerance acquisition. This finding highlights the relevance of compliance in the treatment of patients with IgE-mediated cow's milk protein allergy. Although the magnitude of the odds ratio was high, the model showed statistical stability and an absence of relevant collinearity among the included variables. Nonetheless, the effect estimate should be interpreted with caution, because the retrospective nature of the study and the ordinal categorization of treatment adherence may amplify the effect size in this type of analysis.
Allergic comorbidities were associated with a lower probability of tolerance acquisition. This finding may suggest a higher basal atopic burden in certain patients. However, the retrospective design prevented precise establishment of the temporality between the appearance of these comorbidities and the tolerance evaluation, as well as differentiation of their clinical severity. In this context, the observed association should be interpreted primarily as a possible prognostic marker of atopic susceptibility.
Limitations of the study include its retrospective design, the non-randomized assignment of feeding regimens, and the performance of open oral provocation tests. Although these tests were carried out under the supervision of pediatric allergists and following objective clinical criteria, observer bias cannot be completely ruled out, particularly in mild clinical manifestations. Likewise, the population analyzed comes from a private pediatric allergy clinic, which may limit the extrapolation of the results to other healthcare contexts with different access to specialized care.
Despite these limitations, the study systematically integrates clinical data, feeding regimens, and objective parameters of skin reactivity in a longitudinal cohort of Mexican infants with IgE-mediated cow's milk protein allergy. Taken together, these findings provide relevant observational evidence to contextualize the nutritional strategy for this disease in real clinical settings and contribute to generating hypotheses that should be evaluated in prospective studies with greater methodological robustness.
CONCLUSIONS
The elimination diet was associated with the acquisition of immunological tolerance in approximately two-thirds of infants with IgE-mediated cow’s milk protein allergy (CMPA) at the 12-month follow-up. No statistically significant differences were identified between feeding regimens in the rate of tolerance, so the superiority of a specific regimen cannot be established.
The higher proportion observed in the group receiving exclusive breastfeeding should be interpreted as a descriptive finding. Adherence to dietary treatment was the main factor associated with the acquisition of tolerance after multivariate adjustment, while allergic comorbidities were related to a lower probability of clinical cure.
Casein was the allergen with the highest initial reactivity and showed significant reduction after dietary intervention in all groups. In contrast, a family history of atopy showed no association with the acquisition of tolerance.
Together, these findings provide relevant local clinical evidence for decision-making in the treatment of Mexican patients with IgE-mediated cow’s milk protein allergy, and underscore the need for prospective studies that allow for the establishment of causal relationships with greater methodological robustness.
Declaraciones
Conflicts of interest
The authors declare no conflicts of interest.
Funding
This study received no funding from any external source.
Ethical responsibilities
The procedures performed in this study adhere to the ethical principles governing human research in accordance with the General Health Law regarding research in Mexico. Likewise, they were conducted in accordance with institutional ethical standards and the 1964 Declaration of Helsinki and its subsequent amendments or comparable standards. As this is a retrospective observational study based on a review of clinical records, the study is considered to be of no risk to participants and did not require individual informed consent. Confidentiality and anonymity of the information were guaranteed at all times, protecting personal data in accordance with current regulations.
Authors’ contributions
Hannia Bertha Matt Hernández: Conceptualization, study design, data collection, database creation, analysis and interpretation of results, writing of the original manuscript, and general project coordination. Virginia María González Pérez: Data collection, database creation and review, clinical supervision, methodological support, and critical review of the manuscript. Víctor Soto Torres Septién: Data collection, support in the creation and validation of the database, data analysis, scientific review of the manuscript, and approval of the final version.
All authors participated actively in the development of the study, critically reviewed the manuscript, and approved the final version for publication.
Key references
Bognanni A, Fiocchi A, Arasi S, et al. World Allergy Organization (WAO) Diagnosis and Rationale for Action against Cow’s Milk Allergy (DRACMA) guideline update XII: recommendations on milk formula supplements with and without probiotics for infants and toddlers with cow’s milk allergy. World Allergy Organ J 2024; 17 (4):100888.Nowak-Wegrzyn A, Mehr SS, Katz Y, et al. The multiple facets of cow’s milk allergy. J Allergy Clin Immunol Pract 2024; 12 (1): 12-21.Nachshon L, Goldberg MR, Epstein-Rigbi N, Katz Y, Elizur A. Long-term outcome of IgE-mediated cow’s milk allergy and risk factors for persistence. J Allergy Clin Immunol Pract 2025; 13 (2): 369-377.
Permissions
All figures and tables presented in this manuscript are original and were created by the authors based on the data obtained in this study. No previously published material that requires authorization for reproduction was used.
Permissions
All figures and tables presented in this manuscript are original and were created by the authors based on the data obtained in this study. No previously published material that requires authorization for reproduction was used.
Conflictos de interés
Los autores declaran no tener conflicto de intereses.
Financiamiento
El presente estudio no recibió financiamiento de ninguna fuente externa.
Responsabilidades éticas
Los procedimientos realizados en este estudio se apegan a los principios éticos que rigen la investigación en seres humanos conforme a la Ley General de Salud en materia de investigación en México. Asimismo, se realizaron de acuerdo con los estándares éticos institucionales y con la Declaración de Helsinki de 1964 y sus enmiendas posteriores o estándares comparables. Al tratarse de un estudio observacional retrospectivo basado en revisión de expedientes clínicos, el estudio se considera sin riesgo para los participantes y no requirió consentimiento informado individual. En todo momento se garantizó la confidencialidad y anonimato de la información, resguardando los datos personales conforme a la normativa vigente.
Contribución de los autores
Hannia Bertha Matt Hernández: Conceptualización, diseño del estudio, recopilación de datos, creación de la base de datos, análisis e interpretación de resultados, redacción del manuscrito original y coordinación general del proyecto. Virginia María González Pérez: Recopilación de datos, creación y revisión de la base de datos, supervisión clínica, apoyo metodológico y revisión crítica del manuscrito. Víctor Soto Torres Septién: Recopilación de datos, apoyo en la creación y validación de la base de datos, análisis de datos, revisión científica del manuscrito y aprobación de la versión final.
Todos los autores participaron activamente en el desarrollo del estudio, revisaron críticamente el manuscrito y aprobaron la versión final para publicación.
Referencias clave
Bognanni A, Fiocchi A, Arasi S, et al. World Allergy Organization (WAO) Diagnosis and Rationale for Action against Cow’s Milk Allergy (DRACMA) guideline update XII: recommendations on milk formula supplements with and without probiotics for infants and toddlers with cow’s milk allergy. World Allergy Organ J 2024; 17 (4):100888.Nowak-Wegrzyn A, Mehr SS, Katz Y, et al. The multiple facets of cow’s milk allergy. J Allergy Clin Immunol Pract 2024; 12 (1): 12-21.Nachshon L, Goldberg MR, Epstein-Rigbi N, Katz Y, Elizur A. Long-term outcome of IgE-mediated cow’s milk allergy and risk factors for persistence. J Allergy Clin Immunol Pract 2025; 13 (2): 369-377.
Permisos
Todas las figuras y tablas presentadas en este manuscrito son originales y fueron elaboradas por los autores a partir de los datos obtenidos en el presente estudio. No se utilizó material previamente publicado que requiera autorización para su reproducción.
Permisos
Todas las figuras y tablas presentadas en este manuscrito son originales y fueron elaboradas por los autores a partir de los datos obtenidos en el presente estudio. No se utilizó material previamente publicado que requiera autorización para su reproducción.
REFERENCIAS
- 1.Warren CM, Jiang J, Gupta RS. Epidemiology and Burden of Food Allergy. Curr Allergy Asthma Rep 2020; 20 (2): 6.
- 2.El-Hodhod MA, El-Shabrawi MHF, AlBadi A, et al. Consensus statement on the epidemiology, diagnosis, prevention, and management of cow’s milk protein allergy in the Middle East: a modified Delphi-based study. World J Pediatr 2021; 17 (6): 576-589.
- 3.Sicherer SH, Sampson HA. Food allergy: epidemiology, pathogenesis, diagnosis, and treatment. J Allergy Clin Immunol 2018; 141 (1): 41-58.
- 4.Peters RL, Allen KJ, Dharmage SC. The natural history of food allergy. Curr Allergy Asthma Rep 2020; 20 (12): 68.
- 5.Nowak-Wegrzyn A, Mehr SS, Katz Y, et al. The multiple facets of cow’s milk allergy. J Allergy Clin Immunol Pract 2024; 12 (1): 12-21.
- 6.Nowak-Wegrzyn A, Sicherer SH, et al. Food allergy and anaphylaxis guidelines update. J Allergy Clin Immunol 2020; 145 (4): 1082-1123.
- 7.Sánchez A, Sánchez J, Cardona R. Resultados y limitaciones de los estudios epidemiológicos sobre alergia alimentaria en ciudades del trópico. Rev Alerg Mex 2019; 66 (1): 9-17.
- 8.Domínguez V, et al. Prevalencia de alergia alimentaria en estudiantes universitarios de Guadalajara. Rev Alerg Mex 2019; 66 (4): 394-401.
- 9.Ortiz-Fonseca E, Hernández-Soto A. Alergia a la proteína de la leche de vaca. Rev Alerg Mex 2025; 72 (4): 318-330.
- 10.Fiocchi A, Dahdah L, Albarini M, et al. Diagnosis and management of cow’s milk allergy: DRACMA guideline update. World Allergy Organ J 2022; 15 (5): 100648.
- 11.Bognanni A, Fiocchi A, Arasi S, et al. World Allergy Organization (WAO) Diagnosis and Rationale for Action against Cow’s Milk Allergy (DRACMA) guideline update XII: recommendations on milk formula supplements with and without probiotics for infants and toddlers with cow’s milk allergy. World Allergy Organ J 2024; 17 (4): 100888.
- 12.Koletzko S, Niggemann B, Arato A, et al. An ESPGHAN position paper on the diagnosis, management and prevention of cow’s milk allergy. J Pediatr Gastroenterol Nutr 2024; 78 (2): 386-413.
- 13.Vandenplas Y, Brough HA, Fiocchi A, et al. Current guidelines and future strategies for the management of cow’s milk allergy. J Asthma Allergy 2021; 14: 1243-1256.
- 14.Caffarelli C, Baldi F, Bendandi B, et al. Cow’s milk protein allergy in children: updated practical guide. Ital J Pediatr 2020; 46: 114.
- 15.Lifschitz CH, Szajewska H. Cow’s milk allergy: current evidence for diagnosis and management. Eur J Pediatr 2018; 177 (1): 3-13.
- 16.Vandenplas Y, Munasir Z, Hegar B, et al. Hydrolyzed rice formula in infants with cow’s milk protein allergy: a systematic review. Nutr Rev 2021; 79 (5): 493-502.
- 17.Dupont C, Chouraqui JP, de Boissieu D, et al. Dietary treatment of cow’s milk protein allergy in infants: systematic review and recommendations. Clin Rev Allergy Immunol 2020; 59 (3): 412-428.
- 18.Sorensen K, Cawood AL, Gibson GR, Cooke LH, et al. Amino acid formula containing synbiotics in infants with cow’s milk protein allergy: a systematic review and meta-analysis. Nutrients 2021; 13 (3): 935.
- 19.Donovan SM, Dewey KG, Novotny R, et al. Maternal diet during pregnancy and lactation and risk of child food allergies and atopic diseases: a systematic review. Alexandria, VA: USDA Nutrition Evidence Systematic Review; 2020.
- 20.Wasserman RL. A diagnostic approach to IgE-mediated food allergy: a practical algorithm. J Food Allergy 2024; 6 (1): 15-20.
- 21.Lozano NA, Marini VN, Monferini F, Pury S, et al. Alérgenos de leche de vaca: características moleculares y relevancia clínica. Methodo Investig Appl Cienc Biol 2025; 10 (4): 4-12.
- 22.Lee ECK, Trogen B, Brady K, Ford LS, et al. The natural history and risk factors for the development of food allergies in children and adults. Curr Allergy Asthma Rep 2024; 24 (3): 121-131.
- 23.Nachshon L, Goldberg MR, Epstein-Rigbi N, Katz Y, et al. Long-term outcome of IgE-mediated cow’s milk allergy and risk factors for persistence. J Allergy Clin Immunol Pract 2025; 13 (2): 369-377.
- 24.Díaz-Martín JJ, Martín-Masot R, Santamaría-Orleans A, Navas-López VM. Cow’s milk protein allergy: ETAPA survey on pediatric management and tolerance acquisition. Children 2025; 12 (12): 1645
- 25.Santos AF, Brough HA. Making the Most of In Vitro Tests to Diagnose Food Allergy. J Allergy Clin Immunol Pract 2017; 5 (2): 237-248.